Gastric sleeve cost is never a single figure. A bariatric estimate is an assembly of separately priced components: the hospital or surgical facility; the anaesthesia team; the planned inpatient stay; the pre-operative workup; the surgical hardware; the structured follow-up programme that runs for years afterwards. Most published headline numbers describe only the first three items. Reading a bariatric quote well means reading a set of line items rather than a price tag. This guide explains what sits behind each component plus the questions that expose an incomplete estimate. No figures appear here because a responsible estimate follows a clinical assessment rather than preceding one.
Key Takeaways
- A bariatric estimate is built from six independent components. The pre-operative workup plus long term follow-up are the two most often missing from a headline number.
- Insurance rules cause a wider swing between two patients than surgeon fees ever do.
- Lifelong vitamin plus mineral supplementation is a permanent budget line, confirmed by British Obesity and Metabolic Surgery Society monitoring guidelines.
- Revision surgery is priced separately from a primary procedure. Long term sleeve gastrectomy series document revision as a recognised outcome.
- International Plus has treated more than 200,000 patients from 140+ countries since 2014 under Turkish Ministry of Health authorisation.
What Determines Gastric Sleeve Cost in Practice?
Six variables carry most of the variation between two estimates for the same operation. The hospital setting is the largest single driver since an accredited inpatient facility with intensive care capacity prices differently from a same day surgical centre. Anaesthesia complexity ranks second because obstructive sleep apnoea lengthens monitored recovery time.
Planned inpatient nights form the third variable. Fourth comes the pre-operative workup: endoscopy; blood chemistry; cardiorespiratory clearance; a psychological assessment. According to Mechanick JI, et al., 2020, perioperative nutrition plus metabolic support is a clinical requirement before bariatric procedures rather than an optional extra. Surgical hardware such as stapling devices forms the fifth variable. The sixth is a structured follow-up programme, which a serious unit prices for at least 12 months. In practice, the surgeon fee is rarely the reason two estimates diverge. Our coordination team sees the workup line move most often after an endoscopy finding.
Which Components Sit Inside a Gastric Sleeve Surgery Cost?
A complete gastric sleeve surgery cost estimate separates what happens before the operating room from what happens inside plus afterwards. The table below groups the six components the way a bariatric coordinator should present them so a patient can see which lines are fixed at quotation stage.
Two categories matter more than the rest. Lines fixed at quotation cover theatre time; the ward bed for planned nights; the surgeon plus anaesthetist fees; baseline laboratory work. Provisional lines cover an intensive care night; a repeat investigation after a finding; reinforcement material chosen during surgery; extended nutritional support. Our clinical coordinators issue a revised written estimate whenever a provisional line becomes real rather than absorbing the change quietly. The operating room is predictable. The assessment around the operating room is not.
| Component | Usually fixed at quotation | Usually provisional until assessment |
|—|—|—|
| Facility and theatre | Standard theatre time; ward bed for planned nights | Intensive care night if comorbidities require one |
| Clinical team | Surgeon plus anaesthetist fees | Additional specialist review such as cardiology |
| Pre-operative workup | Baseline bloods; endoscopy; imaging | Repeat testing after a finding; sleep study |
| Consumables | Stapling devices; standard sutures | Reinforcement material chosen during surgery |
| Follow-up | Scheduled dietitian plus surgical reviews for year one | Extended psychological or nutritional support |
| Long term | Not usually included | Lifelong supplementation; annual bloods |
Does Insurance Cover Gastric Sleeve Surgery?
Insurance coverage is the widest source of variation in what a patient personally pays. Policies differ on whether metabolic surgery is a covered benefit; on the documentation required for pre-authorisation; on which preparatory items sit inside the approval. Gastric sleeve cost with insurance therefore describes a co-payment rather than a total.
Many plans that approve the operation still exclude the psychological assessment or the dietitian programme. Two patients in the same ward can face very different bills purely because one policy classifies a pre-operative endoscopy as diagnostic while the other classifies the same test as elective. Ask for the exclusion list in writing before any deposit is paid. A coordinator who produces that list has finished the administrative work. Insurance status also changes timing since pre-authorisation adds weeks or months to a surgical schedule. For example, a cardiology clearance requested late can push a planned date by a full quarter.

What Changes the Cost of Gastric Sleeve Without Insurance?
Self funded patients face different arithmetic. The cost of gastric sleeve without insurance concentrates every component into one payable figure, which makes the exclusions matter more than the inclusions. Three items commonly sit outside a self pay package: an unexpected finding during pre-operative endoscopy; an unplanned additional inpatient night; a complication managed after discharge.
A self pay pathway suits a patient with a clean workup and a stable schedule but the same structure is not right for someone with significant cardiac or respiratory comorbidity because optimisation before surgery may add investigations that no fixed package anticipated. Docimo S Jr, et al., 2024 published a cost comparison between GLP-1 receptor agonists and bariatric surgery, modelling where the two pathways break even over time. That comparison belongs to a treating physician rather than to a price list. Medical alternatives are evaluated clinically, never selected from a website.
Why Does Revision Surgery Sit Outside the First Quote?
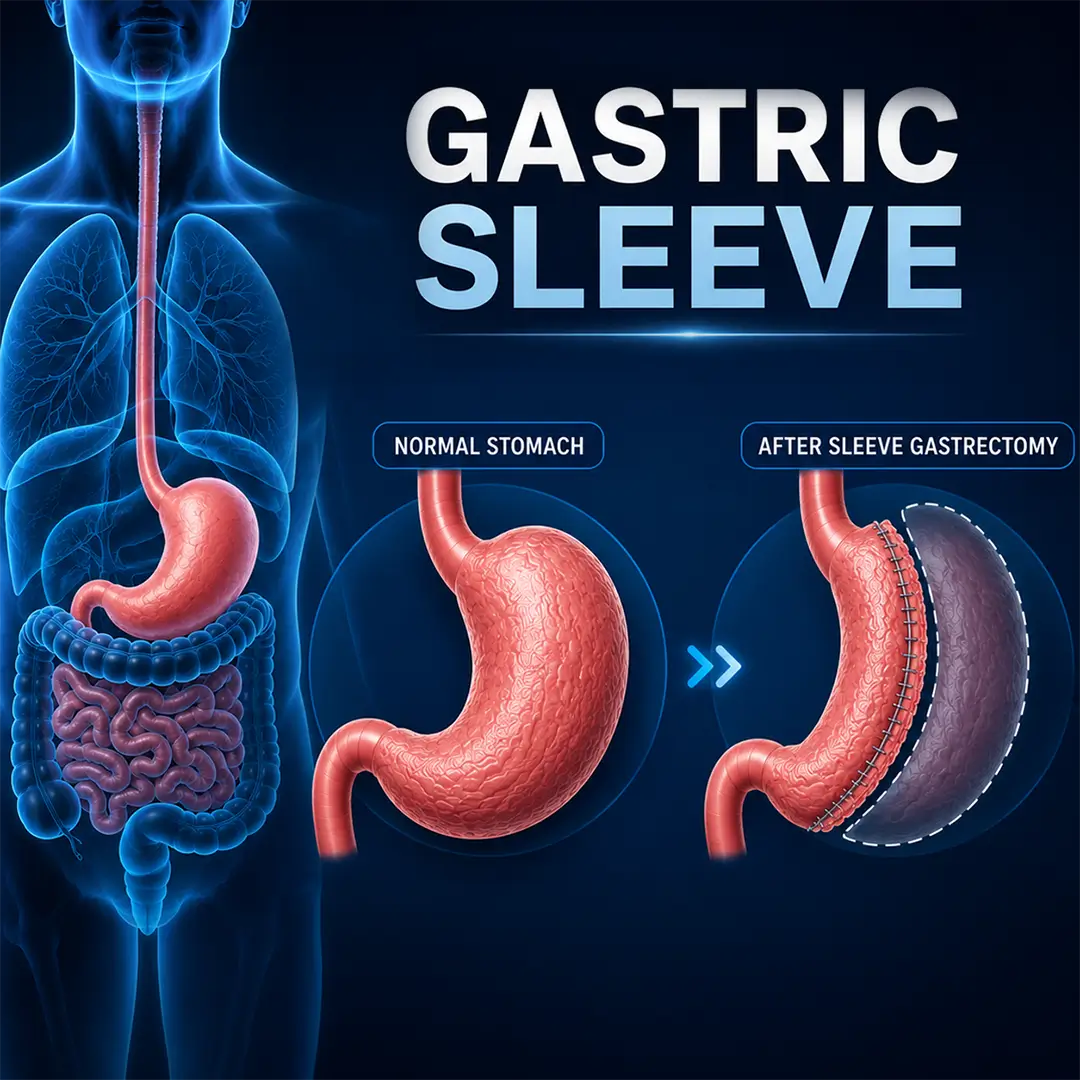
Revision is a separate operation carrying a separate price so no primary quote can include revision honestly. Long term research documents that a proportion of sleeve patients later undergo conversion, most often to a Roux-en-Y conversion for insufficient weight loss or for reflux resistant to medical management.
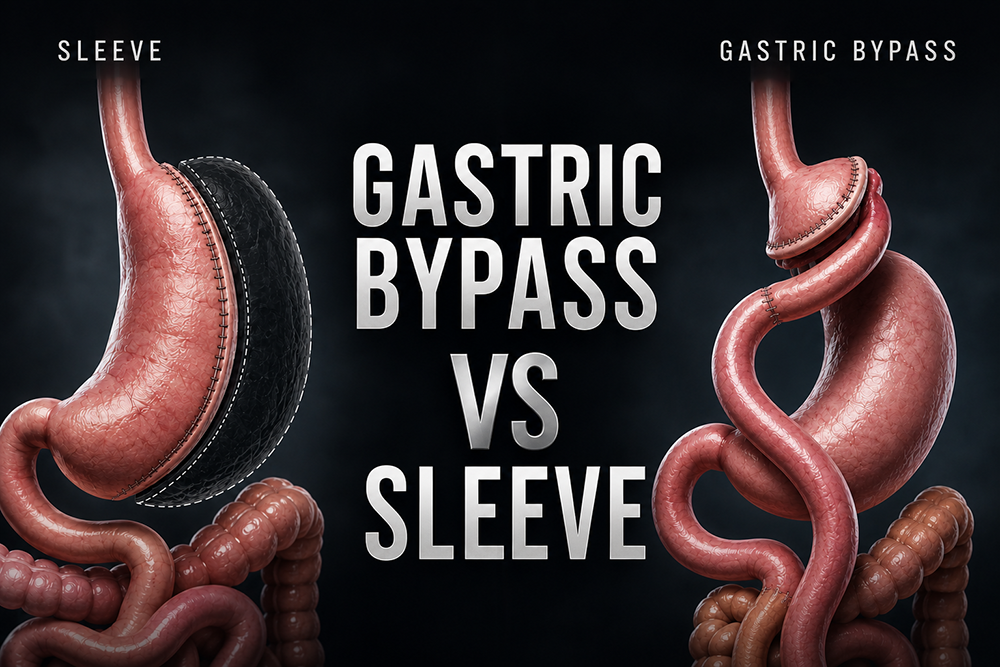
Studies show revision is a recognised part of the treatment landscape rather than a failure narrative. Sakran N, et al., 2023 published a long term matched comparison of primary and revisional laparoscopic sleeve gastrectomy. Clapp B, et al., 2018 reported a thirteen year experience covering surgical risk; weight loss; revision procedures. Budgeting for the possibility is more useful than assuming the possibility away. Patients weighing the two main operations against each other will find the anatomical trade-offs set out in our comparison of gastric bypass vs sleeve.
What Lifetime Costs Follow the Operation?
Three recurring costs continue for life after any sleeve gastrectomy. Micronutrient supplementation is the first and is not negotiable since a reduced gastric reservoir changes intake plus absorption of several vitamins and minerals. Annual blood testing is the second recurring cost. Structured dietetic review is the third.
Research shows the monitoring schedule is lifelong rather than temporary. O’Kane M, et al., 2020 published British Obesity and Metabolic Surgery Society guidelines on perioperative and postoperative biochemical monitoring plus micronutrient replacement for bariatric patients. Tabesh MR, et al., 2023 set out an updated practical guideline on nutrition; physical activity; supplement prescription before and after bariatric surgery. Dietetic review matters most during the first 24 months when eating patterns are rebuilt. A quote ending at discharge has priced an operation rather than a treatment programme.
How Do Country and Hospital Structure Change the Figure?
Cost structure varies between health systems because labour; facility overheads; device pricing all vary. Economics rather than quality drives that gap and the difference cuts both ways. A lower national cost base can fund the same accredited theatre, the same monitored bed, the same device inventory.
The variable worth examining is continuity of care: who manages the first year of follow-up; who reads the annual bloods; who is accountable if a complication develops after the flight home. Galvain T, et al., 2023 modelled cost effectiveness of bariatric surgery inside a national health system, treating downstream care as part of the calculation. Patients comparing destinations for any procedure will recognise the framework in our guide to comparing treatment destinations plus our broader medical travel decision framework. Accountability after discharge is the real comparison.
Which Questions Should You Ask Before Accepting a Bariatric Quote?
Six questions separate a planned estimate from a marketing figure. Start by asking what happens to the price if pre-operative endoscopy shows a hiatal hernia. Ask whether the quoted inpatient nights are a minimum or a maximum. Ask who pays for an additional monitored night.
Three further questions close the gap. Ask which follow-up appointments are included plus for how many months. Ask what written discharge file the patient receives for a physician at home. Confirm what the unit does if a complication appears six weeks later. International Plus coordinates patients in 21 languages and holds a 4.8/5 rating across 5,504 verified reviews, a verifiable record worth checking before any deposit. The same transparency logic appears in our analysis of what drives a treatment price abroad plus our breakdown of all inclusive package structures.
Reading a Gastric Sleeve Cost Estimate With Clear Eyes
A useful gastric sleeve cost estimate is dated; itemised; conditional on an assessment that has already happened. A serious estimate names the facility; the planned nights; the workup; the follow-up window; the exclusions. No honest programme forecasts a weight outcome because individual results vary between patients.
Candidacy itself, including body mass index thresholds plus comorbidity criteria, is decided by a multidisciplinary team after full evaluation rather than by a price list. Readers wanting the procedure explained before looking at any figure can start with our guide to what a gastric sleeve involves. Those weighing a non surgical first step can review the gastric balloon pathway. International Plus combines Turkish Ministry of Health authorisation with 5,504+ verified reviews at 4.8/5 plus 200,000+ international patients across 140+ countries, delivering its gastric sleeve programme inside that multidisciplinary structure. Travel logistics appear in our overview of transfer and accommodation planning.
Frequently Asked Questions
Why do published gastric sleeve prices differ so widely?
Published figures describe different scopes. One number may cover theatre plus surgeon only while another includes the workup; inpatient nights; a year of follow-up. Facility type, anaesthesia complexity plus length of stay then add further variation. Comparing two figures without comparing their inclusion lists produces a meaningless result.
Does insurance usually cover a sleeve gastrectomy?
Coverage depends entirely on the individual policy and jurisdiction. Some plans treat metabolic surgery as a covered benefit after documented criteria are met while others exclude parts of the pathway such as psychological assessment. Pre-authorisation is normally required. Request the written exclusion list from both insurer and clinic before committing.
Are vitamins and follow-up included in a sleeve quote?
Rarely and never for life. Most quotes include scheduled reviews for a defined period, commonly the first year. Lifelong micronutrient supplementation plus annual biochemical monitoring are separate recurring costs described in published bariatric guidelines. Treat both as a permanent budget line rather than an optional extra.
How is revision surgery priced?
Revision is quoted as a distinct operation after a fresh assessment since the anatomy; the operative difficulty; the hospital requirement all differ from a primary case. Long term series report revision as a recognised outcome in a proportion of patients. No primary quote can responsibly include revision in advance.
Does a lower national price mean lower quality care?
Not by itself. Facility overheads, staffing costs plus device pricing differ between health systems for economic reasons unrelated to surgical standards. The meaningful checks are accreditation; surgical volume; intensive care availability; accountability for follow-up. Verify those items directly rather than inferring quality from a number.
Who decides whether someone is suitable for surgery?
A multidisciplinary team decides, typically including a bariatric surgeon; an endocrinologist; a dietitian; a mental health professional. The evaluation reviews body mass index, comorbidities plus previous weight management attempts and psychological readiness. No website, calculator or price list can make that determination.
Reviewed by Dr. Eren Gülbahar
References
- Mechanick JI, et al. Obesity (Silver Spring). 2020. PMID: 32202076
- O’Kane M, et al. Obes Rev. 2020. PMC7583474
- Tabesh MR, et al. Obes Surg. 2023. PMID: 37389806
- Docimo S Jr, et al. Surg Endosc. 2024. PMID: 39285034
- Galvain T, et al. Diabetes Metab Syndr Obes. 2023. PMC10075262
- Sakran N, et al. Obes Surg. 2023. PMC9809525
- Clapp B, et al. Surg Obes Relat Dis. 2018. PMID: 29625744
Follow us on Social Media
internationalplusofficial
internationalplus
internationalplusdental
This content is written, reviewed, and approved by the International Plus Medical Review Board to ensure clinical accuracy and adherence to strict editorial standards. All medical information is regularly monitored, audited and updated in light of the latest scientific advancements.
However the information provided here is for general informational purposes only and cannot be used for self diagnosis or making individual health interpretations. Results of medical treatments depend on individual anatomy and the unique healing process of each patient. This information should not replace a personal consultation with a qualified healthcare professional. To understand the best options for your specific needs and to receive a personalized treatment plan, we invite you to book a free consultation with the expert medical team at International Plus.

I am a healthcare professional with over 4 years of experience in dentistry, specializing in prosthetic dental treatment and implant-based applications. Since 2024, I have been serving as chief physician, leading clinical management, team coordination, and international patient processes. With my B2-level English proficiency, I am able to communicate effectively with international patients. I am a patient-centered, innovative, and solution-oriented dentist who prioritizes patient satisfaction.